
Procedure
Rotator cuff repair
Medically reviewed by Dr Kalman Piper, FRACS (Orth). Last reviewed 16 May 2026.
Arthroscopic re-attachment of torn rotator cuff tendons to the humeral head with suture anchors. Restores the lifting and rotating mechanics of the shoulder when the cuff has torn off the bone.
Watch · 6 min video
Rotator cuff repair surgery
How a torn rotator cuff is repaired through keyhole surgery, what the anchors and sutures do, and the six months of recovery.
Read the transcript
Introduction
This is Dr Kalman Piper's guide to rotator cuff repair: how the operation is done and what the recovery involves.
Treatment options
The first treatment option is always non-operative, meaning without surgery. That's cortisone injections and physiotherapy. It can settle the pain down, but it won't fix the tear. For older, less active people, that's often a good option. For younger, active people, a tear that's left alone tends to stay weak, the pain is more likely to come back, and there's a risk of arthritis in the shoulder down the track. That's when Dr Piper recommends surgery to fix the tendon.
Keyhole surgery
The operation is called an arthroscopic rotator cuff repair. Arthroscopic means keyhole. It's done through two or three small incisions, and you usually stay in hospital overnight.
Preparing the footprint
First, the surgeon roughens up the footprint with a gentle scrape. That gets it bleeding and creates a healing response, so the bone behaves as if the tear is fresh.
Suture anchors
Then the surgeon puts a series of suture anchors into the bone. They look like plastic, but they're made of a high-tech material that dissolves over time and turns back into bone. Each one carries a big, strong suture.
Tying the tendon down
The sutures are passed through the torn tendon and used to tie the tendon back down onto the bone. The ends of the sutures aren't cut. They're fed into a second row of anchors in the side of the bone, which presses the tendon flat onto the footprint. Seen from above, each knot sends one suture limb to each of the second-row anchors, so the sutures cross over the top of the tendon and oppose more tendon onto the bony footprint. That's the rotator cuff repair.
Why the repair needs protecting
Unfortunately that repair isn't very strong. Imagine a torn, ratty tendon end with a few stitches through it, and a big, strong muscle at the other end that can normally lift ten or twenty kilos with the arm out straight. If you do too much too soon, the tendon strips straight out of the repair, so the repair has to be protected with restrictions after surgery, to reduce the risk of it tearing again.
Slow healing
So the job of rehab is to protect the repair while your body heals the tendon back to the bone. That healing process is slow, because tendon has almost no blood supply. The tendon slowly grows lots of little fibres back into the bone to reattach itself. Imagine a tree trying to grow its roots into a rock. Overall it takes about six months for the tendon to fully heal to the bone and for the bond to get back to full strength.
The rehab timeline
After the operation you wear a sling for six weeks. Then you start physio, which usually runs for three to four months. Initially you might see the physio once or twice a week, but towards the end of the program, you might be seeing them every two or three weeks and do the exercises yourself, at home. The repair is most at risk in the first three months, so early physio is range of motion only, and the restrictions are strict. By three months, the tendon has healed to the bone sufficiently that the lifting limit can go up and your physio can start a graduated strengthening program. Most people are back to normal use at six months.
The restrictions
For those six months there are three restrictions. No heavy lifting: two kilos when you first come out of the sling until month three, and five kilos from three months to six months post surgery. No repetitive shoulder movements, like digging, sweeping or vacuuming. And no overhead work. The main rule is simple. If it makes the shoulder sore, don't do it.
Biceps tenodesis
Two other steps are often done at the same time as the rotator cuff repair. The first is a biceps tenodesis. The biceps muscle has two tendons at the shoulder called the long and short heads. The short head has a straight line of pull from the shoulder down to the elbow. The other, the long head, is a thin tendon that does a ninety-degree turn as it exits the shoulder, right next to where the cuff tears. It often gets inflamed and causes pain down the front of the arm. In a tenodesis, it's stitched into the repair and the inflamed portion is removed. That doesn't change the strength of the biceps at the elbow. It just moves where the long head attaches, and stops that pain.
Acromioplasty
The other step performed with a rotator cuff repair is an acromioplasty. The acromion is the part of the scapula or shoulder blade that sits over the top of the shoulder like a roof, and forms the point of the shoulder. Some people have a flat undersurface. Some have a curve, and some have a small hook or spur that catches when you lift the arm up. That catching sensation is called impingement. A few millimetres are shaved off the undersurface of the acromion to give the shoulder more room to move.
AC joint resection
If your AC joint is inflamed and causing pain, an AC joint resection can be performed at the same time as the rotator cuff repair. The AC joint is where the collarbone or clavicle meets the acromion, right on top of the shoulder, about where a bra strap or bag strap sits. The resection removes the very end of the collarbone so the two bones stop rubbing.
Close
This short video describes the surgery and the rehabilitation required. Every surgery carries risks which will be discussed with you before your surgery. There's also information on the risks of surgery at kaliper.com.au. If you have questions about your own shoulder, Dr Piper can go through them with you at your consultation.
Indications
When rotator cuff repair is the right operation
Not every rotator cuff tear needs surgery. Many partial tears and some smaller full-thickness tears settle with non-operative treatment. Surgery is considered when:
- An acute traumatic tear in a younger patient. Earlier repair gives the best chance of tendon healing and a good long-term result.
- A full-thickness tear with weakness or significant pain. Particularly when the tear is interfering with sleep, work, or daily function.
- A partial tear that has not responded to physiotherapy. After three to six months of conservative treatment.
- Progressive tears. Some tears get bigger over time. Repair before the tear becomes massive or irreparable can preserve options later.
- Active patients with high functional demands. Manual workers, sportspeople, and patients who need full overhead function for their occupation or activities.
The decision is individual. Tears in older patients with low functional demand and degenerative tears that have been present for years may not benefit from repair, even if they are full-thickness. In those cases, non-operative treatment, or in advanced cases a reverse shoulder replacement, may be the better option.
How it works
How the repair holds the tendon to the bone
The rotator cuff tendons normally insert into a footprint of bone on the humeral head. When the tendon tears off, the goal of repair is to bring the tendon back to that footprint and hold it there while it heals.
The fixation is done with suture anchors. Each anchor is a small screw-in or push-in device with sutures threaded through it. The anchor is placed into the bone of the humeral head, and the sutures are passed through the torn tendon and tied to bring the tendon down onto the footprint.
For most tears, two rows of anchors are used (a double-row repair). This recreates a broader contact area between the tendon and the bone, which improves the chance of healing.
The procedure
What happens in the operating theatre
The procedure is performed under general anaesthetic, usually with a regional nerve block to help with post-operative pain control. The patient is positioned in a beach-chair position, and the operative arm is prepped and draped free.
Two or more small skin incisions are made around the shoulder. A camera (the arthroscope) is placed through one of the portals, and instruments through the others. The shoulder joint is examined first, then the bursa above the cuff is cleared so the tear can be assessed.
The torn edge of the tendon is freed up so it can be brought back to the bone without tension. The bone footprint is prepared. The anchors are placed into the bone, and the sutures are passed through the tendon. The sutures are tied to bring the tendon down onto the footprint.
Other associated problems are addressed at the same time. Common examples include trimming the undersurface of the acromion if there is impingement, treating biceps tendon damage with a tenotomy or tenodesis, and treating AC joint arthritis if symptomatic.
The skin incisions are closed with absorbable sutures. A sling is applied at the end of the procedure. Most patients stay one night.
Recovery
What recovery looks like
The sling is worn for six weeks to protect the repair while the tendon heals back to the bone. Passive exercises (movement of the shoulder without using the shoulder muscles) start within the first week or two under physiotherapy guidance. The aim is to maintain range of motion without putting load through the repair.
Active movement out of the sling progresses through weeks six to twelve. Strengthening is introduced from around three months, starting with very light resistance and building up gradually.
Most patients can drive at six weeks once out of the sling and with safe two-handed control of the steering wheel. When you can go back to work depends on your job and the size of the tear. The guide below is for most patients.
Strength and range of motion continue to improve for six to twelve months after surgery. The repair is at its weakest in the first three months and gets stronger as the tendon heals to the bone.
Returning to work
| Type of work | When |
|---|---|
| Desk work | 8 weeks |
| Light manual work | 12 weeks |
| Full duties | 6 months |
Light manual work means no lifting over 5 kg, no overhead work, and no repetitive shoulder or arm movements such as digging or sweeping.
These times are a guide only. They depend on your job, and on what Dr Piper finds and repairs at your operation. Check with him before you go back.
Complications and risks
What can go wrong
Arthroscopic rotator cuff repair is a well-established procedure with generally good outcomes. The specific risks include (but are not limited to):
- Re-tear of the repair. A repaired tendon is never as strong as a healthy tendon. Re-tear rates depend on the size of the original tear, the quality of the tendon and muscle, and the patient's compliance with the rehabilitation. Re-tear rates can be significant in larger tears.
- Stiffness. A period of stiffness after sling removal is normal and improves with physiotherapy. A small number of patients develop significant stiffness that needs further treatment.
- Frozen shoulder. A specific condition that causes pain and stiffness in the shoulder. The condition is self-limited (gets better by itself) but recovery from frozen shoulder can take 12 to 18 months or more.
- Persistent pain. Some patients have ongoing pain after surgery, particularly if there are other associated shoulder problems that were not fully addressed.
- Infection. Very rare with arthroscopic shoulder surgery.
- Nerve injury. Rare. Stretch injuries to the brachial plexus from positioning are uncommon and usually recover.
- Complex regional pain syndrome (CRPS). A rare condition that causes pain and stiffness in the hand.
- Anaesthetic complications. Discussed separately with the anaesthetist before surgery.
- DVT. Very rare with surgery of the upper limb.
Videos
More rotator cuff videos
Why a torn tendon can't heal on its own, and how the shoulder works.
Rotator cuff
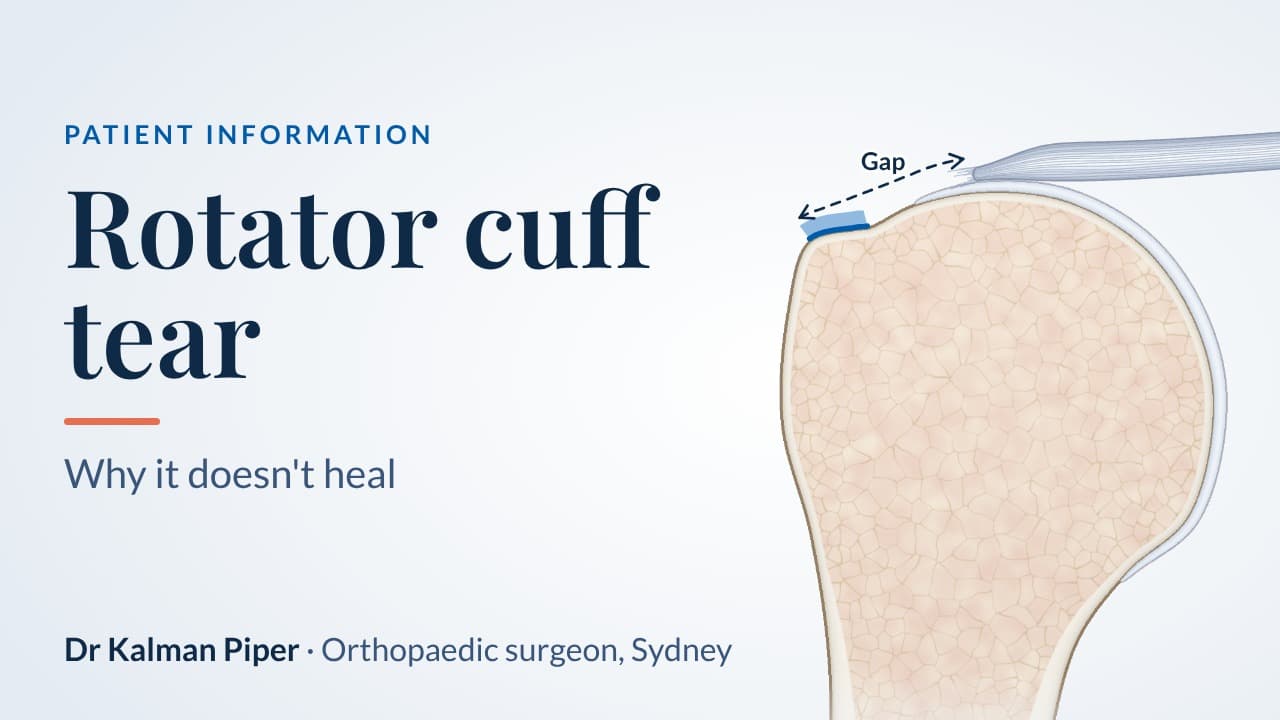
The rotator cuff tear
What a rotator cuff tear is, why the torn tendon can't heal back to the bone on its own, and what causes the pain.
Rotator cuff
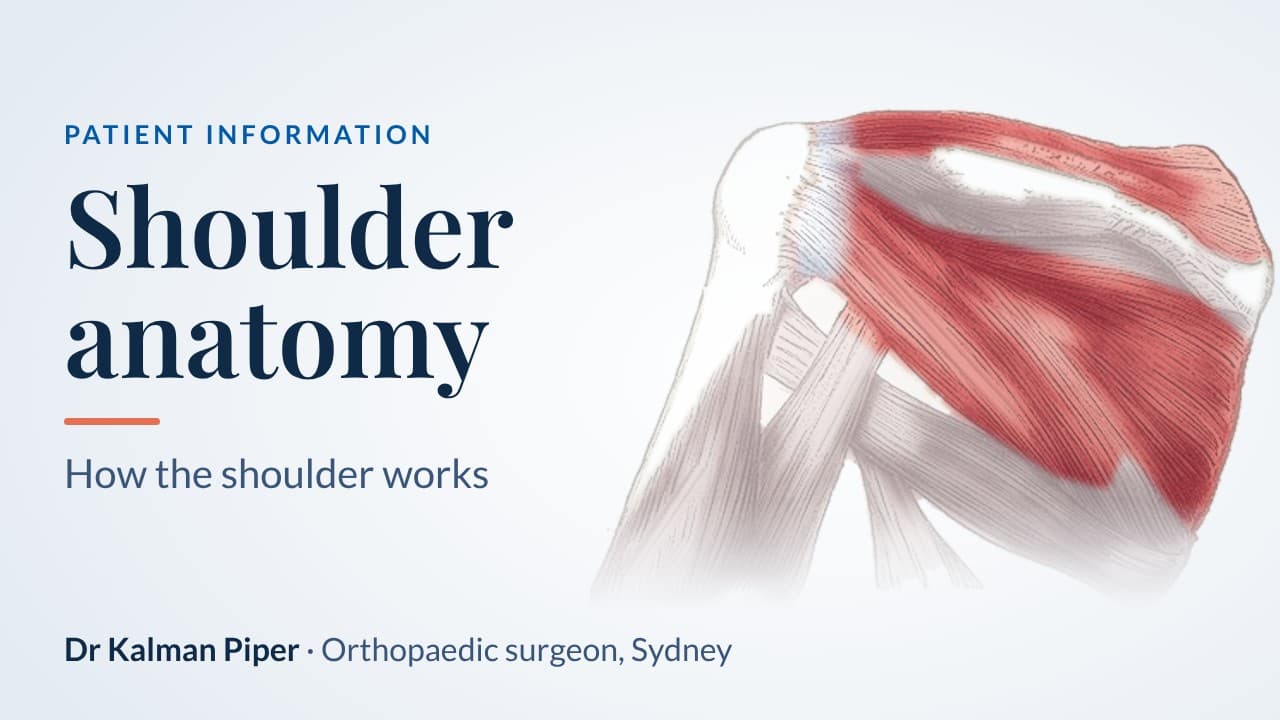
Shoulder anatomy
How the shoulder works: the ball and socket, the labrum and capsule, the four rotator cuff tendons, and the bones and deltoid around the joint.
FAQ
Frequently asked questions
- How long is recovery from a rotator cuff repair?
- A sling is worn for six weeks to protect the repair while the tendon heals back to the bone. Passive exercises start within the first week or two. Active movement progresses through weeks six to twelve. Strengthening starts around three months. Most patients can drive at six weeks once out of the sling and with safe two-handed control of the steering wheel. Strength continues to improve for six to twelve months.
- When is rotator cuff surgery indicated rather than physiotherapy?
- Surgery is considered for acute traumatic tears in younger patients (earlier repair improves healing), full-thickness tears with significant weakness or pain, partial tears that have not responded to three to six months of physiotherapy, progressive tears, and active patients with high functional demand. Many small partial tears settle with non-operative treatment alone.
- What is a re-tear, and how common is it?
- A re-tear is when the repaired tendon detaches from the bone after surgery. A repaired tendon is never as strong as a healthy tendon. Re-tear rates depend on the size of the original tear and the quality of the tendon and muscle. For larger tears, re-tear rates can be significant. Smoking also increases the risk of re-tears. Compliance with the rehabilitation protocol matters.
- Will I get full strength back after rotator cuff repair?
- Most patients regain most or all of their strength, but the timeline is slow. Strength continues to improve for six to twelve months after surgery. Some patients with massive or chronic tears retain mild residual weakness even after a successful repair. The closer the tendon and muscle quality at the time of repair, the better the long-term strength.
- Is the repair done arthroscopically?
- Yes. Dr Piper performs rotator cuff repair arthroscopically, through two or more small skin incisions, using a camera and instruments inside the shoulder joint. The torn tendon is freed up, the bone footprint is prepared, and suture anchors are placed in the bone with sutures passed through the tendon to bring it back to the footprint.
- When can I return to work after rotator cuff repair?
- As a guide, desk work is usually possible at 8 weeks, light manual work at 12 weeks, and full duties at 6 months. Light manual work means no lifting over 5 kg, no overhead work, and no repetitive shoulder or arm movements such as digging or sweeping. These times are a guide only. They depend on your job, and on what Dr Piper finds and repairs at your operation. Check with him before you go back.
Related on this site